


“Did Mom eat today… or did she just think she did?” When someone has dementia, missed meals usually aren’t stubbornness. Memory, attention, vision, taste and judgment all change, and the steps around a plate stop running on autopilot.
This guide covers why meals get skipped, the red flags worth a call today, and the fixes that actually help at the table. It won’t prescribe a special diet — the goal is steady, balanced nutrition that protects strength, mood and immunity.
Why mealtimes stop working

Memory and recognition
A person may not recognize a fork, plate or cup. They might sip from a bowl or use a spoon like a fork. They’re not being difficult — this task is difficult.
Too many choices
A full plate can feel like a crowded to-do list. In middle and later stages, fewer options often calm a person and increase how much they eat. Simple plates and one course at a time help the brain focus.
Reduced taste and smell
Food that once delighted can suddenly “taste like nothing.” Favorite meals may no longer trigger interest at all.
Low energy, mood and agitation
Low mood cuts appetite, and agitation rises when meals are rushed, noisy or unpredictable. A predictable time and place lowers the stress that gets in the way of eating.
The most common reasons meals get missed
Meals are often missed not because someone won’t eat, but because the steps around a plate feel unknown.
- They believe they already ate. They insist breakfast happened, or seem genuinely surprised when offered food.
- They don’t know what to do with the plate. The brain won’t link the steps — pick up, scoop, chew, swallow. This apraxia-like pattern leaves a full plate untouched.
- Utensils have become hard. Odd grips, cutting on the wrong side, giving up in frustration. These look like resistance but are skill breakdowns.
- Their mouth hurts. Jaw-touching, wincing, avoiding crunchy items, tiny sips, bad breath. Dentures that slip or hurt can rule out many foods.
- A medication changed. Appetite shifts often follow a new pill or dose change — call the prescriber rather than “powering through.” The same routines that steady medication habits in dementia tend to steady meals too.
| Cause | What you may see | Care action |
|---|---|---|
| Believes they ate | Insists meal happened; repeats the question | Offer small, familiar snack; note timing |
| Apraxia-like steps | Food present but not used | Hand-over-hand help; single-item servings |
| Utensil trouble | Wrong grip; frustration | Try adaptive utensils; simplify plate |
| Dental/dry mouth | Wincing; avoids crunchy food | Dental check; offer moist, soft foods |
| Medications | New appetite change | Review meds with prescriber |
Red flags worth a call today
Unplanned weight loss in an older adult is serious — losing pounds usually means losing muscle and resilience, and it raises the risk of falls, slow wound healing and infection. If clothing fits more loosely or energy drops, act sooner rather than later.
For dehydration, check at home for minimal or dark urine and fewer bathroom trips, dry mouth, lightheadedness or a rapid heart rate, and new fatigue, dizziness or constipation. Poor food and fluid intake can also make a person more confused, irritable and restless, so track a few days rather than judging one meal.
Don’t wait. If they skip a full day or two of eating and drinking, or you see rapid weight loss, severe thirst, repeated choking or a sudden jump in confusion, call a clinician.
Check for simple causes before you change the diet
Before swapping textures or adding supplements, look for a medical or situational cause. Common hidden ones: constipation, a urinary tract infection, mouth sores, gum disease, ill-fitting dentures, or pain the person can’t explain. Watch for grimacing while chewing or a hand pressed to the belly.
Then keep a short log for three to seven days. Note the time each meal goes best, where they sit, the noise level, who is present, which foods work, and what happened right before — a short walk or light chore can help, and fatigue usually worsens appetite later in the day. A simple caregiver check-in schedule makes that easier to keep up.
Call a doctor for rapid weight loss, dehydration, choking or sudden confusion; a dentist for jaw pain, loose dentures or persistent mouth pain; and ask a registered dietitian about nutrient-dense snacks and safe calorie increases that don’t feel like pressure. For a concise clinical checklist you can use now, see this mealtime assessment guide.
Set up a calmer table
- TV off and phones away; minimal distracting talk.
- Plain tableware — no centerpieces or extra condiments.
- Bright, even light, a solid placemat and a contrasting plate so food is easy to see.
- One course at a time, two choices at most.
- The same chair and routine each day, and plenty of time — a meal may take up to an hour.
Make eating easier: foods, textures and tools
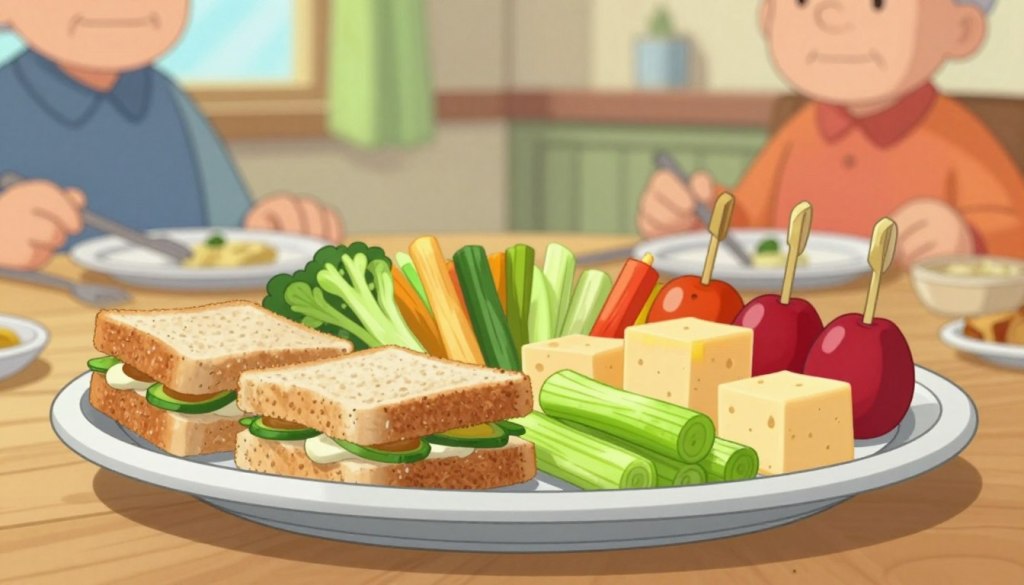
Cut foods into quarter-size bites and remove bones, toothpicks and garnishes. Finger snacks work well for roaming or short attention spans: cheese cubes, small sandwiches, chicken strips, fish sticks, sliced fruit, steamed veggie wedges.
Use a rimmed plate on a non-slip mat, spill-resistant cups with lids, and a single large-handled utensil rather than a full setting. For prompting, use one step at a time: “Scoop.” Pause. “Bring it to your mouth.” Model the action calmly. For hand-over-hand help, ask permission first, then guide their hand through the motion slowly.
Don’t fight the mess. Protect clothing, focus on nourishment, and keep independence where it is still safe. The Alzheimer’s Association has more mealtime detail in its food and eating guide, and Alzheimer Society of Canada covers day-to-day mealtime care.
Watch swallowing as dementia progresses
Swallowing changes quietly make meals unsafe. During meals, watch for coughing or choking, a wet or gurgly voice after swallowing, food “pocketing” in the cheek or very prolonged chewing, and frequent throat clearing or repeated swallowing attempts. Repeated choking, fast weight loss, dehydration or fear of meals warrants a call to the clinician right away.
Favor soft, moist foods; grind or puree when needed; cut bites small and add sauce or broth to dry items. Avoid dry, crumbly or tough foods that scatter in the mouth — raw carrots, hard candies and whole nuts are common high-risk items.
Seat the person upright with feet supported and the head slightly forward. Never tilt the head back during a swallow. After the meal, gently check the mouth for leftover food; pocketing is easy to miss and can cause choking later.
Hydration, constipation and bathroom fears
Thirst slips by unnoticed, and small sips work better than big glasses. Tie sips to the day — after meds, after a walk, during a favorite show — and use small cups or bottles for pacing. When plain water is refused, high-water foods help: fruit, brothy soups, smoothies, milkshakes.
If drinking has dropped off, ask about the bathroom. “If I drink, I might not make it” is a real fear. Validate it, then add clear bathroom signs, night lights, a lit path, or a bedside commode. Constipation itself lowers appetite and raises agitation, so keep fluids, fiber and movement together, and review medications with the clinician if low intake or constipation persists.
“I already ate” — what to say instead of arguing
That phrase can mean many things: they believe it, they’re embarrassed, they’re tired, the plate looks overwhelming, they don’t recognize the food, or they want the conversation to stop. Treat it as information, not a debate, and offer a soft reset:
- “You may be right. I brought a small snack just in case.”
- “That’s okay. Let’s just have tea and a few bites.”
- “No big meal. Just a little yogurt.”
Where you can, stop asking “Did you eat?” — it puts the weight on memory. Ask about right now instead: “What’s on your plate?” “Can you take a sip while we talk?” “Is the blue bowl empty or full?” “Would you like the soup or the yogurt first?” These tell you what is actually happening without asking the person to reconstruct the whole meal. If pressure has crept into meals, dropping the question is often the fastest fix.
Work out which kind of support is missing
When reminders stop working, don’t add more reminders — change the type of support. Meal problems usually fall into one of four gaps.
Try JoyCalls Free
No app or new device needed. Start with a free 7-day trial.
- Memory gap. They can eat safely but forget the meal exists or believe they already ate. Scheduled calls, a visual meal board, labeled containers and a confirmation after meals usually carry this stage.
- Initiation gap. They see the food but don’t start — staring, moving food around, getting distracted. Sit with them for the first few minutes, give one-step prompts, offer one food at a time, start with a small bite, or eat beside them so they can copy the action. A note is no longer enough here.
- Physical comfort gap. They want to eat, but pain, dry mouth, swallowing trouble, constipation, fatigue or a medication is in the way. This one needs a dental review, a medication review, softer and moister foods, a swallowing assessment or dietitian guidance — don’t guess for long.
- Safety gap. They can’t manage meals alone: choking, appliances left on, spoiled food, confusion with hot liquids. Supervised meals, ready-to-eat food only, in-home care visits or an occupational therapy home safety review. This isn’t taking independence away; it’s preventing harm while keeping as much choice as possible.
The useful question is not “How do we make them remember?” It’s “What support removes the need to remember?”
Your next step: a three-day meal reality check
Before you change anything big, write down three days. For each meal: what time food was offered, what it was, how much was eaten, how much fluid was taken, whether reminders were needed, whether they ate alone or with someone, any coughing, pocketing, pain or refusal, and their mood and energy around it.
Keep it brief — you don’t need a perfect food diary, just enough to see the pattern. Three lines can tell you a lot:
- Monday lunch: chicken soup and toast. Ate half with one reminder. Small glass of water. No coughing. Seemed tired.
- Tuesday lunch: sandwich on the table. Untouched after two hours. Said she already ate. Drank tea only.
- Wednesday lunch: yogurt and banana during a phone call. Ate all the yogurt, half the banana. Needed step-by-step prompting.
That is not a diet problem. That is a timing, simplicity and cueing problem — and it is the kind of detail a doctor, dietitian or home care provider can act on immediately.
If it would help to have someone check in at mealtimes, JoyCalls makes a friendly phone call at the times you choose, asks a few simple questions, and sends you a short summary afterward — including an alert if the call is missed. Learn how JoyCalls works or call 1-415-569-2439 to hear a sample call.

Ana Avila is a writer who covers the everyday challenges of supporting older adults: staying connected, checking in regularly, remembering medications, maintaining routines, and helping family caregivers stay informed without feeling overwhelmed.
Her work for the JoyCalls blog focuses on the practical side of aging at home and family caregiving. She writes about loneliness and social connection, wellness check-ins, medication reminders, memory support, caregiver stress, aging in place, and the ways AI companions and voice technology can provide consistent support between visits and phone calls. Most of her articles start with a simple question: what is a family caregiver worried about today, and what practical steps can make that situation easier?
Ana writes for people who are busy and often juggling caregiving with work, family, and their own responsibilities. Her guides are designed to be easy to understand, useful right away, and grounded in the realities of caring for an aging parent or loved one. She avoids jargon, explains technology in plain language, and is careful not to oversell what any tool, including AI, can do.
A consistent theme in her writing is that technology should strengthen human connection rather than replace it. The measure of a good system, in her view, is simple: does an older adult feel less alone, does a family member have greater peace of mind, and does a caregiver have more time and energy for the moments that matter most.
